Thursday, October 30, 2014

The vestibular system and vision

I've been reading up on the link between vision and the vestibular system. It's been quite instructive to say the least. Of course it's annoying not to be able to align the eyes and have double vision while reading etc... However, there's more. It's very interesting how compromised eye movements, in large part due to eye muscle surgery, and consequently a compromised Vestibulo-Ocular Reflex are likely to be the biggest source of disability and fatigue for me personally. When going beyond my relatively low visual endurance limit, the sensory conflict between the visual and the vestibular gets exacerbated. It sometimes feels like being drunk and can even give me something resembling to a hangover later on. Not merely alignment of the eyes but also the integration of these ocular motor skills with the vestibular system will be crucial in terms of lasting vision therapy results and daily functionality.

What is the vestibular system?

- Peripheral
The term 'vestibular' comes from the Latin 'vestibule' which means room. This 'room' is located in the inner ear and contains a minute amount of chemical fluid. Its workings involve the detection of fluid movement by receptor hair cells in various differently oriented semicircular canals. Vestibular injury may or may not be accompanied by hearing loss.


- Central
The vestibular sense is often misunderstood or overlooked. That's because, for instance, there is no such thing as a primary vestibular cortex.

'There is, rather, a complex of cortical targets many of which remain difficult to understand. From the brainstem, vestibular signals reach a subcortical structure called the diencephalon. Tucked in between the cerebral hemispheres the diencephalon houses such important structures as the pineal gland, hypothalamus, and thalamus. Compared to the cerebral cortex the diencephalon is small in size but is very rich in nuclei for sensory, motor and limbic pathways. The thalamus is a central relay station for all incoming sensory signals excepting olfactory information.' - Vision Rehabilitation

Without going into detail, we can conclude this sense is for a large part located in the primitive,  reptilian part of our brain which houses many basic but vital functions. In fact, this sense is so essential to our functioning and well-being, that the vestibular nerve is the first fiber tract in the brain to begin myelination during pregnancy. This process starts by the last week of the first trimester. By the end of the fifth month of pregnancy, the vestibular organ has reached full size with ongoing myelination of pathways to the eyes and the spinal cord.

- Function
Whereas the anatomy and chemistry of the vestibular system itself are fascinating, its interaction with the visual system and other somato-sensory systems are even more interesting.

The vestibular system is responsible for
(1) detecting linear and angular head movement and head position in space;
(2) assisting gaze stabilization of the visual field;
(3) maintaining balance and postural control; 
(4) providing spatial orientation or perception of body movement.

The primary role of the vestibular system is to provide the brain with information to regulate posture and to coordinate eye and head movements. Proper vestibular functioning and integration with the other senses is of major importance to good overall health, optimal functionality and vision.

Link with vision?

'The vestibular system plays an important role in the generation of eye movements that compensate for head movements. Through vestibular nuclei in the brainstem, each SCC (semi-circular canal) is able to communicate with motor neurons of extra-ocular muscles to cause eye deviation in each canal’s own plane. This interaction is the basis of the vestibuloocular reflex (VOR), which stabilizes gaze upon an image or the visual world during head movement. If the VOR is impaired, loss of gaze stabilization is the result. For example, as the patient turns the head while walking an object in the visual field or the whole visual environment appears unsteady or “bouncing.”

Demer described the VOR as a “synergistic” interaction between the vestibular and ocular systems. Normal VOR stabilization is needed for “functional vision, and vision optimizes the performance of the VOR”. Dynamic visual acuity (DVA) plays a role in maintaining a sharper image on the retina, while the VOR steadies gaze during head movement. This interaction is called the visual vestibuloocular reflex (VVOR).' - Vision Rehabilitation
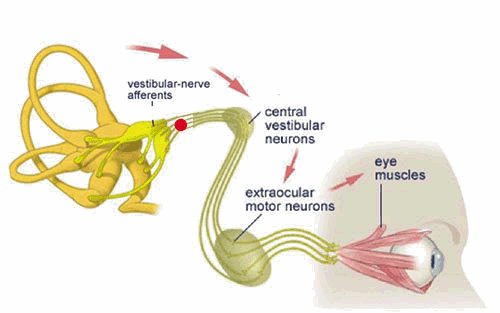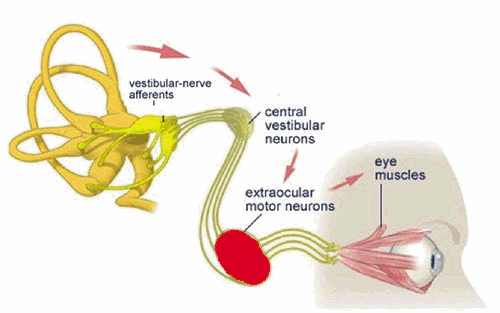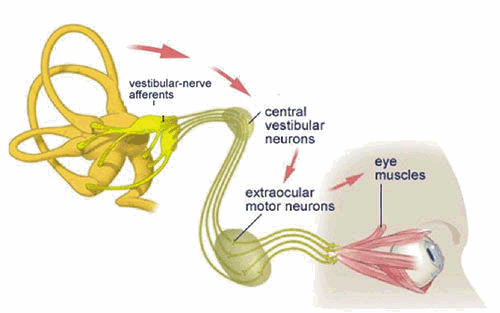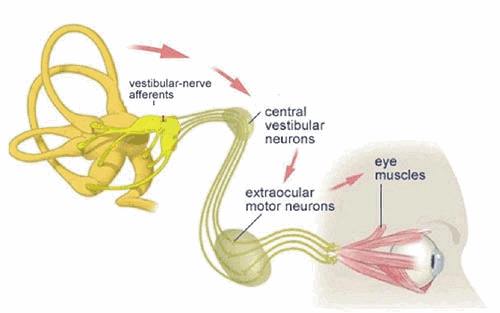


And in turn...

'Sensory receptors in the eyes provide important feedback regarding orientation of the body in space. In other words, where is the head in relation to the horizon? As discussed in Chapters 5 through 7, dysfunction in the visual perception of “straight ahead,” common following brain injury, can cause dizziness, disorientation, and imbalance. In the process of orientation, visual input also provides information regarding possible environmental hazards, barriers or avenues of escape. In the presence of impaired inputs from either the somatosensory (sensory projections from all over the body) or vestibular or both systems there is a strong dependence upon visual input. Defective input from one of the three systems (visual, proprioception/somatosensory, vestibular) may be compensated for by the remaining intact systems such that the patient is able to function, albeit with some discomfort and loss of efficiency. However, dysfunction in two of the three systems will result in significant disability.' - Vision Rehabilitation

Problems?

Even though the vestibular sense might often be overlooked by physicians, one will be made aware of its existence in case of dysfunction.

- Inappropriate nystagmus
'Spontaneous nystagmus, occurring when the head is static (still), is an indicator of acute peripheral vestibular loss. Nystagmus is often along the horizontal plane. Vertical or torsional spontaneous nystagmus usually indicates a direct injury to the brainstem. The cause of this inappropriate nystagmus is a direction-specific imbalance in the VOR as brainstem neuronal circuitry is activated. Inappropriate nystagmus may also be related to medication toxicity, such as some antiseizure medications.' - Vision Rehabilitation

Inappropriate nystagmus may also be provoked by head shaking and indicates an imbalance of dynamic vestibular function.

An indicator of inappropriate nystagmus of central origin, caused by brain dysfunction rather than dysfunction of the peripheral organ, is often the inability to inhibit nystagmus with visual fixation.


- Dizziness
Feeling disoriented, especially in dark areas, or feeling spacey, floating, rocking, or lightheaded. Dizziness is not always related to vestibular dysfunction but may indicate non-vestibular causes, one of which being visual disorders. However, when dizziness is mentioned, involvement of a vestibular dysfunction must be considered.

- Vertigo
Even though dizziness and vertigo are often used interchangeably, technically there is a difference. Vertigo refers to the illusion of movement, typically rotational, when no actual movement is observed. True vertigo refers to vestibular system involvement.

- Motion sickness
What causes motion sickness?

'There is a hierarchical preference to rely on visual input more than any one of the other two systems (vestibular, proprioception) involved in balance. Vision, as proposed by Bronstein, had a dominant role or “hierarchical preference” over proprioceptive input in the process of maintaining upright posture and balance. However, Mallinson et al. suggested that a “visual preference strategy” would not apply to some individuals who have an intolerance for any disagreement between visual and vestibular signals. Paige had previously called this disagreement between the two systems as a “visual vestibular mismatch” (VVM) and others referred to it as a “sensory conflict.” By 1996, the “sensory conflict” theory for the development of motion sickness had been accepted within the scientific field studying this subject.' - Vision Rehabilitation

- And more...
Balance problems, gait ataxia, ...

Of the top of my head I can think of two interesting cases I read about involving vestibular dysfunction.

In the book 'The brain that changes itself', Norman Doidge described a woman who felt like she was perpetually falling due to vestibular injury.   Her vestibular organ was damaged but her central vestibular processing capabilities were intact. We can't even start to imagine how she felt. It completely ruined her life. Until a certain Doctor thought of the idea to supply her brain with 'vestibular input' in a different way. He connected an accelerometer to a tongue outlet which gave her a certain signal depending on the direction towards she was falling. Through the mechanisms of brain plasticity she learned to ignore her vestibular organ and to stabilize herself using this new input stream. Somehow over time, as her brain re-calibrated, she became less dependent on the device and needed it less and less.

Another vestibular story was featured in Oliver Sacks' 'The man who mistook his wife for a hat'. A Parkinsonian, 93 year old, retired carpenter whose vestibular sense had become more and more unreliable started walking tilted over to one side without knowing it. His senses deceived him until he saw himself on camera. He was speechless. After this discovery he wondered whether he could apply the mechanism of a spirit level to his problem. He designed a pair of glasses including some sort of spirit level which he could then use to teach himself to walk upright again. Essentially he retrained his impaired vestibular system using visual feedback. At first it took a lot of conscious effort but later on it got easier and easier. Just like learning how to drive a car.

Psychological impact of vestibular dysfunction

'There are a variety of reasons why patients suffering from episodes of vertigo develop anxiety, depression, poor self-esteem, and a growing sense of disability. The fear of falling or the fear of heights is common. Concern for a sudden onset of vertigo and the loss of control in public venues often leads to avoidance behaviors or “safety-seeking behaviors,” as coined by Gurr and Moffat. The appearance of staggering, falling, and confusion may lead observers to believe that the person is intoxicated. The patient soon finds him/herself avoiding social events and staying home to avoid embarrassment. Physical activity is avoided for fear of provoking an episode.' - Vision Rehabilitation


Testing

- Static and dynamic balance testing. Dynamic balance tests require input from the Vestibulo-Ocular Reflex to stabilize the visual field and make rapid adjustments in posture. Dynamic gait, sit-to-stand, ...
- Dix Hallpike maneuver
- Bithermal Caloric irrigation test (COWS): spraying water in the ear. Check it out on Youtube. It's pretty cool.
- Comprehensive Vision Testing: gaze, tracking, binocular vision, perceptual, functional, nystagmography, ...

Please read Chapter 9 of 'Vision Rehabilitation' for more detailed information. 

Rehabilitiation of the vestibular system

Vestibular injury or dysfunction can impose dramatic alterations in a patient’s once active lifestyle. There will be occasions when medication can be helpful in the short term. Surgery is the rare choice. Therapists take caution when a patient has other disabilities (brain trauma, stroke, peripheral neuropathy, spinal conditions, and/or vision disorders), which may limit choices of exercises.

'A key factor in achieving the best outcome will be patient compliance. Education is the greatest tool used by a good therapist to engage a patient’s willing participation in what is usually a difficult treatment program. Between, both, the vestibular therapist and the psychotherapist the patient is assisted in understanding the basics of the dysfunction: Why symptoms occur; the emotional response; and how treatment should help. Initial treatment typically provokes unpleasant symptoms but feeling worse comes before feeling better. Another factor in achieving the best outcome involves adequate intensity and duration of the treatment program.

Progression of function is the best gauge for the effectiveness of treatment. The process of treatment involves strategies for adaptation and substitution by using other strategies, habituation (desensitization), and retraining of balance. As the patient is able, exercises are expanded to include cardiorespiratory conditioning. Goals of vestibular rehabilitation are to (1) optimize compensation in the balance system; (2) habituate abnormal vestibular responses to rapid movements; (3) reduce fall risks by improving balance and postural control; and (4) educate the patient.' - Vision Rehabilitation

Is it a vision problem or vestibular problem?

It's important to figure out whether you are suffering from a vestibular problem with a visual component or a vision problem with a vestibular component. For strabismics who identify with some of these issues, the answer is probably 'a vision problem with a vestibular component'.

That is why in the more advanced stages of Vision Therapy you are not only training eye movement. You are to stimulate your way towards overall sensory and thus vestibulo-visual integration. There's a million ways to skin that cat. Some of the things I do as vision therapy loading: walking, head turns while attempting to keep my gaze stable, walking a beam with yoked prisms, balance board, jumping on a trampoline, standing on my head, running, ...

When my vision tends to go blurry or double and I feel dizzy, it's time to take a break. I flirt with my limit, take sufficient rest and remind myself that sometimes you do have to feel worse before feeling better. Improving these elementary vestibulo-ocular skills does influence and improve more sophisticated and more cognitively taxing ocular motor activities such as reading. The ground is being prepared!

Thursday, October 9, 2014

'The ticking time bomb that split my world in two'

About a week ago me and a man named Ryan Brooks had a thought-provoking conversation on my Facebook wall.  I had just shared my latest blog entry 'The margin of error'. He commented "I always find your posts extremely interesting. I had a bleed in the brain stem which has left me with double vision. This is how I see now."


That is not your every day Facebook comment but I knew the visual phenomenon he was talking about of course. As I'm always open to learning about how other people deal with visual brain problems, I asked him whether he wanted to share more about what happened to him. He was prepared to do so and I am happy for it. Even though our histories are different (developmental vs cerebral incident), we are talking about closely related visual issues and symptoms. Thank you for sharing your incredible story, Ryan!

I present to you, Mr. Ryan Brooks.

Part 1
RYAN: "I am 40 years old. I live in Newcastle NSW, Australia. I was an occupational health and safety manager in the mining industry and traveled the world to places like New Caledonia and New Guinea to name a few. I had only been home for eight weeks when the incident happened. Over a period of three months prior to the bleed I had experienced three separate dizzy spells and racing heart episodes but only lasted for about ten minutes. I attributed it to maybe anxiety due to my stressful job.

The brain bleed happened on the 25th of June, 2012 at 11.15AM, I woke up feeling great and drove down to a cafe on the beach for a coffee. As I walked down the beach to the cafe my vision started to blur and I felt a strange buzzing feeling at the back of my head near the base of the skull. I put it down to still being half asleep. I ordered a coffee and sat at a table outside watching the surf. The buzzing started to get worse. I started to feel like I had butterflies in my stomach and felt increasingly faint. I got up to go to the bathroom to wash my face. As I got to the door... Boom. Suddenly I felt as if pins and needles were penetrating my face. Down my left arm and leg I felt numbness as well as pins and needles. All this combined with a feeling of complete disorientation. I managed to stumble back to the front counter and said "Call an ambulance, I'm having a stroke." Then I passed out over a table. A short while after, I came back to and noticed no one was helping me. I was in a bad way. I remembered there was no phone signal inside so I got on my hands and knees and crawled out the front door. I laid on the path, rang my sister and told her what had happened and for her to call an ambulance. The people at the bar told my sister that they thought I was a drug addict having an overdose. My sister went absolutely ballistic. The ambulance arrived 20 minutes later and off to hospital we went. After some brain scans the doctors realized that I had a bleed in the upper mid brain, which is part of the brain stem. More conspicuously, by merely looking at me, they could see my left eye was turned in so hard towards my nose you could barely see it. "


Ryan and his daughter


 Part 2
"The official diagnosis was a cavernous malformation. In plain English this means that a blood vessel wasn't formed properly at birth and it took 38 years to wear out and rupture. In other words, a ticking time bomb."

MICHAEL: After the incident and the diagnosis, did they do something about that blood vessel?

RYAN: "They did an angiogram and injected ink into my brain which basically gave them a map of all the blood vessels in my brain and of the problematic area of vessels in particular. They didn't do anything because the brain area where it happened is very complex. The vessels in that area of the brain stem are the size of a strand of hair. Fortunately they were not arteries. Doing something to 'fix' it would entail too much risk. An intervention might kill me or give me a major stroke. Instead we opted for yearly brain scans. There's no guarantee it won't happen again."

MICHAEL: How did things proceed from there on out?

RYAN: "After four initial weeks of rehab for partial paralysis down my left side everything started to get back to normal. Sort of... Concerns regarding double vision as a result of the bleed and nerve damage remained.

MICHAEL: Can you describe your current visual situation?

RYAN: "The official definition of the visual dysfunctions caused by the brain bleed goes as follows. Bilateral asymmetrical superior oblique paresis, cranial nerve paresis with convergence retraction nystagmus and some myopia in the left eye. But I would like to try and explain what that really means from my point of view.

From the outside my eye alignment looks normal other than a slight turn of the left eye.  Yet from the inside that's a different story. When I look straight ahead the image of my right eye looks pretty level but the image of my left eye is on a 45 degree vertical angle.The left eye also has very bad torsion.


When I tilt my head up and down the torsion becomes worse.  I have vertical up gaze palsy and so when I try to look up my eyes wiggle. Notwithstanding, when I tilt my head slightly to the right it pulls the torsion nearly square. In that moment my brain relaxes because it almost feels like I have normal and steady binocular vision again. Sadly I can't sustain the binocular posture. It's like a stare and after five seconds my left eye starts to drift.


When I turn my head left and right the images split up and down so I have to patch my left eye. It is very hard after 40 years of normal sight to now have two separate images that 'do what they do'.


When I walk without the left eye covered, the image coming from that eye bounces. So when using my right eye, with my left bad eye covered, the eye's movement compensates for any head movement. The image stays stable and straight (proper Vestibulo-Ocular Reflex). On the other hand, when I close my good right eye and only have to draw on my left eye, the image inadvertently moves up and down following head movement (compromised Vestibulo-Ocular Reflex). Not only does the image move up and down, but it also tilts because of the torsion. It's quite nauseating and throws my balance out. If I walk with only my bad left eye open,  it feels like I'm walking across a very steep hill. The image just bounces around inconsistently.

I have also noticed that the color isn't as good in my good right eye. At night my right good eye doesn't see as well as my left bad eye. Everything is a sort of tinted darker when looking through my right eye.

When I close one eye, my vision feels quite normal. although I had to get used to the difference in depth perception. At night, when there is little light, it feels like my vision is back to normal which stops the headaches. That's the only time my brain isn't fighting to get properly aligned binocular input. Then I can relax.

Considering all the above, using my vision is a very fine balancing act."

MICHAEL: How do you make these example images? Do you use an app?

RYAN: "You are actually the one who inspired me to investigate the internet and thus coming across the apps to help explain what I see to other people. These are the two apps. My Doctor was very impressed with the idea of taking photos of what I see and simulate what I see as I move my head into different directions. The images shift when doing so. This way he can see exactly what I see."


MICHAEL: What kind of treatment have you been getting or participating in?

RYAN: "I have been seeing a strabismus specialist in Melbourne at the Private Eye Clinic by the name of Dr Lional Kowal. I had VT for 12 months. While doing VT I was also going to Melbourne every three months for examinations. The VT pulled my eye nearly back to its normal position but the double vision remained.

After that initial year of VT, I have had five correctional surgeries but none have been successful due to damage to the 3rd, 4th, 6th, 9th and 10th cranial nerve. Every time a surgery was done it had a negative effect on either the vertical or horizontal relative positioning of the images. Unfortunately after five surgeries, two of which were to undo previously performed surgeries which had made my double vision worse, I am back to square one."

MICHAEL: I'm just thinking out loud... You had the incident in June 2012. Then you had one year of Vision Therapy aka Visual Neurorehabilitation. That brings us up to August 2013. So you must have had five surgeries in one year? How did that go? You seemed to be making VT progress, albeit slow. Who proposed the surgery? What did the Doctor tell you about its effectiveness, risks and possible outcomes?

RYAN: "As the double vision wasn't disappearing mainly due to the torsion aspect of my case, the Doctor or Neuro-Ophthalmologist suggested surgery. They explained the risks. He was confident he could give me an improvement.

The first operation was performed on both eyes and made the double vision worse. Five days later that surgery had to be undone.

Another three months later I had more eye muscle surgery on both eyes while being awake using only the use of anesthetic drops. They placed a black letter T on the ceiling and also on the wall in front of me. He started with the left eye. Cutting and manoeuvring the muscle a millimeter at a time. Then he'd wash out the eye, take the eye clamps out and tell me to look at the T and ask if there was any difference. Then he'd sit me up and tell me to look at the T on the wall in front of me and ask whether there was any difference. My response was 'it has adjusted slightly'. So back down for more adjusting. This process went on thee times until he said he couldn't do any more. He stated that if he overstretched the muscle it was irreversible. Next we repeated the same process for the right eye.


It was an extremely stressful experience. I could hear my heart racing. I was boiling hot due to the lights and surgical blankets. To be honest, after you have had your eye ball cut open, the eye muscles cut  and then flushed out with water, the mix of blood and water makes your vision quite blurry. So any indication of what I was seeing was compromised and not really accurate. My eyes kept drifting as my muscles were cut, my vision was blurred and the environment was extremely stressful.

A week later after letting my eyes recover a bit the double vision was worse. Another week later I went in for surgery again in an attempt to undo things. Under total anesthesia this time.

Four months later, one more surgery was done to do some slight tweaking. I was completely under for this one. Whatever the result was, I was going to have to live with it."

MICHAEL: You said 'I am back to square one'. Do you feel the surgeries were just a useless exercise or would you say it deteriorated the situation? I'm asking out of genuine curiosity, not because I myself had a very bad experience with strabismus surgery.

RYAN: "Now it is more or less back to where it was after the brain bleed, although a little different. Looking back I'm glad we gave it a try because now I know that at least we tried. I put my trust in my Doctor and we came out the other side not having gained but not having lost much either. He was a wonderful Doctor and only charged me for the first surgery. All the other surgeries he put through my medical fund at a significant price reduction. That was an incredibly kind gesture and showed that he was more interested in my case than in my money. On top of that I was extremely fortunate to have wonderful friends and family who organized a charity events such as a dinner party, an auction and a golf day. They ended up raising enough money to cover my surgeries, anesthetist, flights, accommodation, check ups, glasses, lenses, ... That all amounted to 30.000 dollars. If they read this, I want to thank Brett & Gail Purcell, Nathan Palmer, Tim & Macushla Spencer, Chad Edwards, Leeanne & Jeremy Symes and many other friends and family members who were involved. I had been 14 months off work so without this bunch of phenomenal friends my treatment would definitely have been cut short. I'm immensely grateful to them all."


Part 3
"Nowadays I'm using a tailor made contact lens that looks normal but really isn't. The outer edges are clear so you can still see the colour of my eye but the area covering my pupil is completely blacked out. I had to have my pupil measured so it looks cohesive with my other eye. This means that I am basically blind in my left eye when I have the lens in. Well, not completely blind... I still get peripheral vision from my left eye as the dot on the lens is a little smaller than my pupil and pupil size is variable depending on light conditions. Therefore, I still wear my glasses.   When I'm not wearing my glasses, I have learnt to ghost the images of my left eye but after a while this gives me head aches. So back on go the glasses! Looking at me you couldn't tell anything is wrong. However, without my blacked out lens and my glasses the double vision still gives me constant headaches. .

In general, my life has changed considerably following my accident. I no longer work in the mining industry. I now work as a disability case manager and spend much more time at home with my beautiful daughter."

Wednesday, September 24, 2014

The margin of error

Interestingly, my strabismus was developmental since the age of three but in a relatively short amount of time I lost many of my adaptations (suppression, strabismic ways of eye teaming) to cope with misalignment of the eyes. First my suppression gradually declined because of life style, i.e. overly zealous studying, and then the way my eyes moved and alternated was abruptly changed through eye muscle surgery. This left me without any reliable adaptation to deal with my abnormally developed visual system.

So the only option then, is pick up the pieces and start all over again. My visual system seems to act as a binocular system that was disrupted rather than a visual system which developed strabismically. It has no real inclination, or possibility for that matter, to go back to monocular viewing, alternation or any of its other former ways. There's a strong incentive to use both eyes, and it's constantly trying to do so, with varying rates of success. It's a binocular system whose inability to move its eyes accurately is cramping its style. Because of its poor handling, my case more resembles strabismus which was acquired later in life through brain injury than that of a developmental strabismic equipped with coping tools safeguarding functionality.
The level of spasticity or lack of control when it comes to eye movement is fortunately declining. It has been declining for some years and every improvement is a win. As can be seen in previous video posts, it's getting harder to spot there is any problem at all! However, automation is the goal, not merely the ability to execute the movements using disproportionate amounts of attention and energy resources.

Despite already increased accuracy and speed, there is still a considerable margin of error when it comes to my eye movements. I can not entirely rely on solid binocularity yet. It's either right or not right, and if it's not right you need to waste extra energy on correction which could have been used for observation and interpretation of visual input. Another issue associated with the continual trial and error, and the exertion it requires, is the build up of tension. Because of the lack of eye muscle control, surrounding areas of my body (face, jaw and gradually the entire body) start to tense up. The efforts to keep my left eye in check and attempts to keep up binocular performance will often result in jaw cramps on the left side and headaches. In order to avoid such an escalation it's recommended to allow for a margin of error and try to cut the visual system some slack.

What activities allow for a margin of error?

Reading vs General Navigation

Given this larger than normal margin of error, I prefer to avoid situations which require specific eye behavior.and do not leave much room for error. An obvious example of such an activity that requires precise and infallible eye movements is reading. There's a number of different ways to read but they all require impeccable eye movement control. That's why reading with audio back-up is much more agreeable with me. There's more room for eye movement error that way.

In contrast, the general observation of a road, square or real life situation can be done using an endless variety of eye behaviors. Some are definitely more effective than others but you can still get around.  For someone whose eye behaviors start looking deceptively normal such activities requiring an accuracy level of 'approximate' are starting to be fine. It's starting to get less overwhelming, less out of control. More ocular control will be very welcome over the upcoming year(s) but it's already quite manageable.

Driving is actually easier than walking or running because my body and head stay more or less in position, especially on a highway. Because the road and the mirrors are much larger than the words on a page while reading, and driving is less cognitively taxing, my current level of eye control is okay for driving. In fact, driving is pretty calming as it allows for staring and the use of peripheral vision.

Individuals vs Groups

The difference between reading, general viewing of scenes and driving is pretty straight forward. Here's something which might be more unexpected, or maybe not. Perhaps people without eye muscle palsy experience this difference too. Meeting with one person is a lot more taxing to my visual system than meeting with a bunch of people. I don't look strabismic anymore so it's not about  appearance. Meeting with one person just doesn't allow for much of an error margin when it comes to eye behavior. When talking to someone you have to look at that person. That's specific. It's likely you will have to hold your gaze steady but every once in a while you have to look away. The social situation dictates your eye behavior and your eye muscle control system better be up to the task. Most people I know and enter in contact with are aware of my vision issues and if I do act a little more peculiar than normal and start staring in the distance, I just explain. No biggy. Nonetheless, I try to keep up the eye contact dance. After all, it's good practice! It's also an important means of communication but you need the physical eye fitness to do it. 

When meeting up with larger groups, there is more room for errors in eye movement. You can just listen to the conversation and stare randomly every so often. Attention is divided and you don't always have to look at the person who's doing the talking. It clearly also depends on how familiar you are with the group. An entirely new group in an new environment is a probable overload. I will have trouble moving my eyes to explore and keep up with the new situation, people and environment, especially over extended periods of time. Not much room for eye movement errors in that case because you'll preferably need your brain to deal with the situation rather than an eye movement deficiency. You're losing attention to something that should be working automatically.

Factors that decrease the margin of error

Short term

When I'm going to do something relatively visually taxing, which includes many daily activities in varying degrees, you want to have me well fed and well rested.

I burn calories like you wouldn't believe and when I get hungry my accuracy diminishes and errors occur more frequently. So I'm eating a lot of the time these days as my appetite returned after a couple of very stressful years. This has a double benefit. It more or less keeps up my visual performance in the short run and makes me look less emaciated in the long run.

Naps seriously improve my vision. Even an half an hour nap will seriously improve my visual performance for the night. Don't be a hero, take naps.

Basically I'm just a baby learning how to see. Now we know why they too eat and sleep all the time.

Long term

Current practice consists of finding ways to allow a margin of error while slowly crushing that same margin as time goes by. Sometimes it is not possible to avoid situations that are too visually stressful. Then I do have to hurt myself by pushing it too far, resulting in tension and headaches. But by minimizing the time I exceed my limit and by granting the visual system relative rest, the comfort zone slowly expands.

Eye control and eye alignment should be invariable but is, in my case, all to often variable. Invariable and reliable eye movement control is a great advantage when executing bottom-up visual processing (taking in new visual scenes and observing them) and top-down visual processing (combining stored memories with what is seen). Virtually any human activity employs these kinds of visual processing. Therefore, I'm very curious about the dormant potential that might be uncovered as the rate of movement errors further declines. Stereo vision, for one.   If I ever want to live a 'normal', independent life, there's no other way but to keep working on accuracy, speed and stability of eye movement.


Eye movement control and the use of glasses for hyperopes

It's still frail and not ready to be stress tested, but it's happening. As my gaze gets steadier and the margin of movement errors declines, there is less need for my glasses. As vergence gets easier, I can focus more on the accommodation aspects of visual training. Seamless interaction and collaboration of vergence and accommodation is crucial to obtain a lasting end result in VT. As I'm farsighted (+2.5 in each eye) this evolution could have been expected. The glasses are more a way of avoiding fatigue and thus gaze instability than a way of providing better visual acuity. In fact, I often have to look over them to read things far away. As gaze stability is maturing I actually see better in daily life without the glasses. Ultimately they will just be reading glasses for near point work. Sometimes it even has a calming effect to take them off, even refreshing in a way. I'm still wearing them daily but every so often I let my visual system have a go on its own. Even though my glasses are rimless, it feels different not to wear them. I can believe people have an easier time seeing 3D without glasses or with contact lenses. Glasses have a way of distorting light and possibly binocular vision. However, I'm not going in heals over head... They are a useful anti-fatigue tool while I acquire more eye movement control. 

Friday, September 12, 2014

Some vision testing in front of the webcam

Inspired by Dr. Charles Boulet's article on the Cover Test, I myself felt like doing some testing in front of the webcam.


First you can see me doing some saccades, or jumping movements, going from one corner of my laptop screen to the other. I started off quite well but then my left eye started lagging and had trouble keeping up. This resulted in some double vision when looking at the right. I slowed down and paid more attention to remedy the problem. In order to reduce 'slippage' my left eye needs to improve its quickness of reaction and accuracy. This will be a key factor in acquiring stereo vision and reliable reading skills.

During the cover test my gaze seems pretty solid. In hindsight, I realize that I should have covered each eye for a longer period of time to see whether it would stay in place. Still, not a bad result in view of where I came from.


In this video I am testing my ocular movement ranges. This slow tracking of the object seems mighty fine. I still feel some strain on particular eye muscles and have to stretch them to the limit but the video looks nearly perfect. There are no obvious restrictions in movement anymore.

I must say it makes me very happy to watch myself performing so well on these basic tests. From the outside I almost look 'normal'. There's no way in hell the untrained eye could tell I've had manifest strabismus for the larger part of my life.

Not a hierarchy of visual skills but a proposed aid for vision testing sequence

Hence I have definitely graduated to the 'Convergence Insufficiency class'. I still have trouble reading, problems with fatigue and trouble keeping up consistent performance (especially while moving) which are common symptoms in 'milder' forms of binocular vision issues. 'Milder' binocular vision issues are still a pain in the ass...  Nonetheless, when talking about convergence insufficiency I often heard professionals say it can be  treated successfully in less than a year. God, I so hope that's true!

As we get closer to a resolution, it is only natural my strabismus became less visible from the outside and more visual change will happen on the inside. That idea is so exciting. The idea of effortlessly pointing your eyes and just being able to focus on what is seen. Can't wait!

Related articles:
- You want more evidence? I'll give you some evidence right here.

Tuesday, September 2, 2014

A wedding without double vision

This weekend I attended a friend's wedding. I enjoyed it immensely. It was a reminder of the fact that not everything in life has to be a struggle. Not everything needs to be difficult. It's nice to see so many happy faces celebrating a joyous occasion.

During the last three years I have gone out of social circulation a bit. This is because I was suffering from all the symptoms you might associate with a severe concussion due to chronically untreated and mistreated strabismus. Social circumstances don't always bend to health and resting needs. It's weird to suddenly need to close your eyes to rest them or have to lie down so I prefer to avoid such situations. It has been hard enough to manage and explain my condition to my in house family. It has often proven challenging not to lose my nerve and get angry at their incomprehension of what is obvious, at least, to me. Certainly when thinking they could have avoided the whole thing by using their own brains. Sometimes Sartre is right. L'enfer, c'est les autres.

I also didn't socialize too often because it doesn't change anything about my peculiar problem, drains my energy and adds to the frustration. I simply have to 'do the time' while not bashing into the walls too much. I have been fairly successful at doing my recovery time without repaying, often unintentional, hurt with hurt. That's the best and most sensible way of doing it. I'm good at restraining myself from doing stupid things.

Still, life goes on.  Everyone else goes on to live their life and you have to start from scratch. While they get to have opportunities, jobs, weddings and babies, I have to teach myself how to read. The wedge has always been there, and I have done a remarkable job of covering it up, but in the end the truth remains. I don't possess the visual motor skills to do even basic reading. High intelligence and impeccable work ethic will only get you so far without those.

Meritocracy is dead. I felt as if whatever I do makes no difference and gets me nowhere in life. No wonder I didn't feel like socializing. I mostly felt furious and alienated. This is why, despite being a sociable person and having lovely friends, I was not always capable of being good company. The last thing I wanted to do is lash out at them for something that isn't their fault. They can't help the fact that they have what I want without even giving it a second thought. They can't help a whole series of ignorant, negligent and blameful people made me squander my youth and are still making me pay for their mistakes. However, irritation is natural when being locked in in your own body. Usually thinking about all this lost time and effort makes me want to throw up. Fortunately I have a good understanding of the situation now and know the only solution for me is to take my losses and build a better visual system.

This weekend I felt differently. It might be because I was able to get through the entire day without running into double vision or insurmountable exhaustion. This made me enjoy the day, the lovely people and the beautiful party. However, I think there's more to it. Even though I'm not exactly aiming for a 'normal' life, it must be nice to be able to function normally. In other words, take your life into your own hands. I think I can eventually attain that freedom. I'll have to work with the delayed time frame but I feel as if there's still hope for me after all. In a recent e-mail conversation with Sue Barry, she told me: "It's amazing how much we were missing visually, but this also gives us the opportunity to keep improving. Although my biggest visual changes occurred when I was in formal therapy in 2002 and 2003, I still strategize with my optometrist a few times a year about new exercises I can practice at home, and my vision continues to improve. I'm 60 years old, and while all my friends are complaining about how they are aging, I'm seeing better. So, there are compensations and -you're right - the best is yet to come."

Being there I could just savor the moment without feeling betrayed by anyone having had 'an easier time' than me. I could be happy for them without thinking about our contrasting lives. I won't have to be a dysfunctional illiterate person without opportunities forever. I too will be okay one day and get out of this mess. Among all those happy people I thought about how far I have already come in recovering the unrecoverable, enjoyed my single vision and smiled. Indeed, the best is yet to come.

Wednesday, August 13, 2014

Session 76: Bring in the periphery

Skills acquired so far
- Smooth eye movements, improved vergence amplitudes and eye alignment
- Improved accommodation amplitudes and continuing improvement with flippers
- Stabilizing Vestibulo-Ocular Reflex
- Being able to judge depth using physiological diplopia and reference cue

Left to do:
- Automation and stamina
- Integration, integration, integration.
- My VT seems to be expecting I'll see some float in the Vectograms rather soon. To accomplish this I have to widen the span of my visual field.  That's hard for me. Most of my life I've been busy suppressing my peripheral vision as an adaptation to strabismus. When I try to include more objects into my field of attention my gaze tends to get unsteady. This happens because my limited attention resource partly shifts from eye alignment to the widening of visual intake. That will be the next hurdle to take. "Bring in the periphery!" as my Italian friend Llaria likes to say.

Nice list of acquired skills though. What a journey it has already been over the last three and a half years... Every summer things look different. I'll keep inching forward and by next summer we'll have some good and honest 'float'. Ha!

Thursday, August 7, 2014

Some of my current home based VT activities

Everything we do or don't do has neurological consequences. That's why everything we do or don't do matters.

It's important to note that these activities are not suitable for every VT patient. Nor are they suitable at any stage in the rehabilitation process. They are suitable for me because my ability to control my eyes has reached a level allowing me to handle these activities without imploding, albeit with appropriate rest. Getting to this stage has taken a long time. I've had to do a lot of boring ground work first. Expanding the range of ocular movements, improving saccades, tracking and so on. VT is an active form of patience.

Another important reason of why these activities are appropriate for me as a VT patient is that my central suppression, especially while moving, is very poor. This means there is a very strong incentive for me to use both eyes and align them, rather than trying to suppress one eye. That's a very important point. Taking that into consideration, this means that I'm ALWAYS doing VT. I'm always trying to align my eyes and see binocularly because there's no alternative as there would be in a strabismic with good suppression. That's exhausting, particularly when trying to get out of an initial post-surgery double vision situation. Yet this might have some advantages at a later VT stage.

So what do I do outside the VT office?

1. Bar reading or, when more tired, listening to a text with TextAloud while tracking the words with my eyes. Even without suppression controls, I know when I'm doing it right when the text doesn't go double. The audio support while reading brings some relieve to my vision while still being able to practice saccades and integrate vision, audio and reading comprehension. Over time I feel like the saccades become easier and the audio support is less necessary. I'm gradually inserting prism and spherical flippers into the process to keep it challenging. So far however, (bar) reading hasn't been particularly easy yet.

2. Wearing a translucent filter on my glasses in order to stimulate my left eye and the neurology behind it. I do it in the morning when I'm relatively crisp. Initially doing this was a serious source of energy drainage. The filter in front of the 'good eye' makes the 'lazy' eye work harder in terms of acuity. It also forces me to acquire more dexterity relying on the more impaired eye. Lastly, there's a higher tendency for my eyes to go EXO with the filter requiring more of an alignment effort. To sum up: it works on acuity, eye motility and general integration of the eye into the nervous system.


3. When having to rest, meaning I just want to stare, I sometimes watch some kind of series or movie. When I'm up for it I use the flippers while watching. It's less tiresome than using them while reading because the eyes are more stationary. In fact, the spherical flippers help to relax my eyes when they are all tensed up. It's like stretching soar muscles.
When watching I also like to put a finger (or a remote) in front of my face. If I see two of them I am sure I'm not suppressing part of the view. (physiological diplopia)

4. Head turns. My Vestibulo-Ocular Reflex hasn't been working properly for a long time. This means that when my head moved, my eyes didn't make the appropriate compensatory movements to maintain a stable world view. This year (my 4th VT year) this has finally been leveling out and my eyes do make the appropriate movements for the world to stay fixed and stable. This new and highly anticipated skill isn't entirely reliable as it often gives way when I get tired. That's why I often check up on it and train it for short intervals by making head turns. My VOR needs further refinement, integration and staying power.

5. Anaglyphs: I play with these cards or other anaglyph visuals when I feel like it. Lately it's more fun because I can figure out the DEPTH in them by using my hand and physiological diplopia as a reference. It helps the learning process of corelating eye posture, image disparity and distance. The needed information is being picked up by my brain but I need to further automate these inferences. In the VT office we also use vectograms.


6. Lately I'm playing a lot of football (soccer), sometimes with the translucent filter in front of my left eye. Movement is good. Interaction with the environment is good. Messing around with a football is good visio-motor exercise. When my eyes stop aligning because of fatigue I notice two footballs and know it's time to call it a day.  It's important not only to get both eyes working together but also to integrate them into a moving body. I put special emphasis on using both feet and both sides of my body, mixing it up and trying to stay aware of the entire visual field and physiological diplopia. Football may not be for everyone but I have some very fond memories of playing football as a child so I try to tap into that. Positive emotions and enthusiasm are very important in terms of motivation and creating new pathways in the brain. 

7. Recently I had ten days of access to a trampoline. You'd think it doesn't really make that much of a difference but it does. When getting off the trampoline the world feels like it's moving beneath your feet. It's similar to disembarking a boat. Trampolines are great to further load and consolidate visio-motor and vestibulo-ocular skills. If that gets easy, you can further load the exercise with cognitive processing. Have a look at this cool exercise: http://www.oepf.org/sites/default/files/journals/jbo-volume-21-issue-3/21-3%20Slotnick.pdf 

8. Yoked prisms. These powerful prisms, used with bases to one side, shift your entire visual field to the direction of your choice. The lenses are adjustable. I use them bases up, down, left and right. By doing so I train internal adjustment to new visual circumstances. More specifically they stress test the brain's ability to ajust its egocentric localization, eye and body posture as well as sense of balance and spatial vision.  I have found them very useful in terms of aligning my subjectively perceived and objective midline which is often an issue in strabismus patients. Be careful with these toys though. Don't use them for more than 10 minutes at a time or you might suddenly get licked. They are effective but exhausting. I don't use them every day either. That said, I've had my most 'unusual' visual experiences after using yoked prisms.


9. Deck of cards exercise. It's similar to the 'classic' accommodative rock exercise. Get yourself two decks of cards. Tape one on the window, hold one in your hand and start scanning the window looking for corresponding cards. Emphasize accuracy, binocularity and physiological diplopia. Do it well rather than fast.


10. Taking walks. As for integration of the eyes into the body walking is perfect. Fast is easy, slow is hard. Running is not bad either but you might be paying less attention to the visuals and wasting a lot of energy that could be used for visual consolidation. Vision first, running later. That's how I see it. While walking, take care of your visual experience: eye alignment, physiological diplopia and just being aware of your body and the view. Don't just go walking around dull-minded with ear-buds. 

11. Being aware of my left side and using my left hand sometimes. As my left eye is my amblyopic eye, my right brain hemisphere needs fitness. This is almost surely a gross oversimplification but nonetheless trying to become more bilateral is part of becoming more binocular. Eg. if there's no time pressure I try to use my left hand. My mother told me that before I developed strabismus and amblyopia due to undetected farsightedness at age three, it was very hard for my kindergarden teachers or herself to tell whether I was left or right handed. I was just using either one. Then when I became strabismic the right side heavily dominated things visually and motorically. The chauvinist left hemisphere started hindering the development of my right hemisphere, visually and otherwise. Apparently, as I'm recovering, this is somewhat being reversed. Sometimes when I'm bored I doodle. Yesterday I was doodling with my left hand and noticed I could draw reasonably well with my left hand too. This is new!

Left hand drawing

12. Thump-Pinky Vergence Rock. An exercise similar to the Brock String. The best thing about this exercise is that it works on the integration of visual and proprioceptive input. This is often a decisive factor in getting ahead.  


13. Doing somersaults with my eyes open until I get dizzy. Usually three. That's another Vestibulo-Ocular Reflex integration exercise.

Obviously these activities are not exhaustive. There are many ways to combine and load activities according to your current level. I also don't do all of them every day. Rather, I try to make whatever I'm doing into a visual exercise. If you have some idea how a healthy visual system is supposed to work, you can aspire to that goal.  Just as important as what you do, is how you do it. In the end, life is just one big visual exercise!

Aside from exercising, I'm also eating a lot. It appears that I have already reached one of the goals I set for next year. In two to three months I've gained 6 kilograms bringing me up to 75kgs. This takes my BMI (height=1,85m) from 19.9 to 21.9.  I'd been trying to gain weight for a long time but I guess I'm finally calm enough for it to stick.
I'm mentally preparing myself for the fact that eliminating the residual Convergence Insufficiency and other visual instabilities up to a workable level will likely take another year to year and a half. With some luck and steady work I'll be an 80kg binocular machine by next year. That reminds me... I need to go eat something!